Why Are Doctors Prescribing an Antidepressant for Sleep? the Truth Behind Trazodone
 By Chloe Bennett
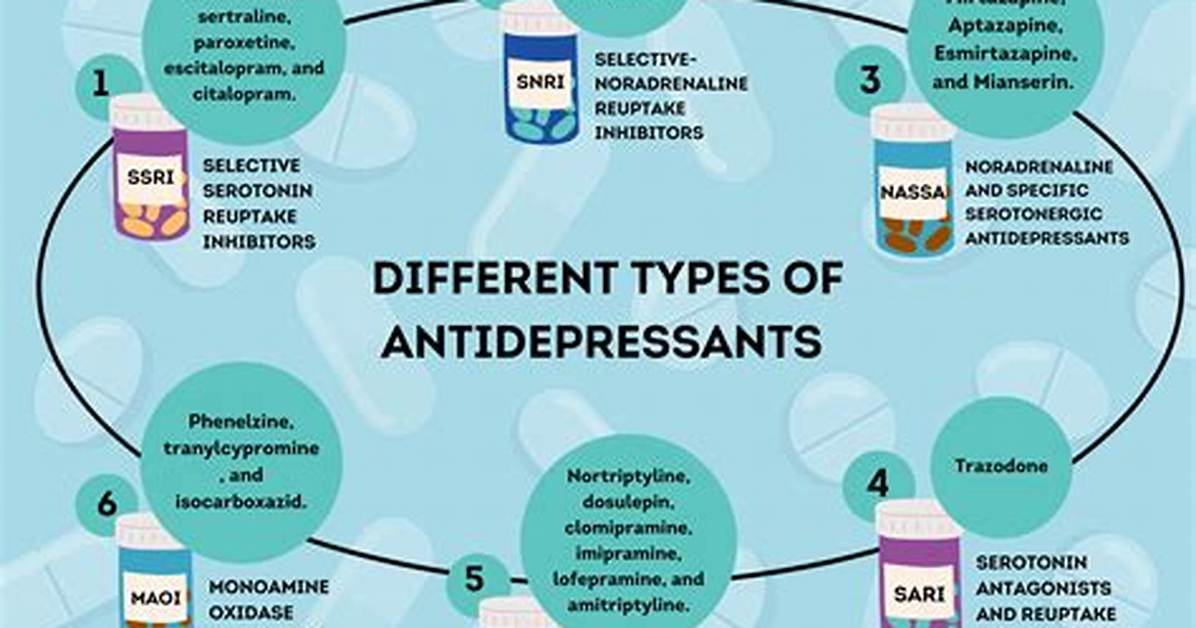
When Italian researchers synthesized trazodone in 1966, they were hunting for a cleaner way to elevate mood. At the time, early tricyclic antidepressants carried severe cardiac toxicity risks in overdose, and medical teams wanted safer alternatives. The U.S. Food and Drug Administration granted approval for trazodone to treat major depressive disorder in 1981. But psychiatrists quickly hit a wall in clinical practice. To achieve true antidepressant effects, patients had to take between 150 mg and 400 mg daily. At those doses, individuals felt so profoundly sedated they could barely keep their eyes open during daylight hours.
By the time selective serotonin reuptake inhibitors (SSRIs) like Prozac took over the psychiatric world in the late 1980s and 1990s, trazodone had largely lost its place as a front-line mood elevator. Yet doctors noticed a valuable silver lining. SSRIs frequently caused acute agitation and severe middle-of-the-night waking. Instead of throwing addictive sedatives at the problem, clinicians started adding tiny doses of trazodone, often just 25 mg to 50 mg, at bedtime. The combination settled the nervous system without neutralizing the primary antidepressant.
What began as an adjunctive trick rapidly evolved into standard primary-care practice. Between 2010 and 2026, prescribing rates for low-dose trazodone surged across North America and Europe, fueled by rising clinician reluctance to hand out controlled substances. Today, while pharmaceutical databases continue to classify the compound under mental health medications, the vast majority of written scripts target sleep maintenance and sleep-onset latency.
Chloe Bennett explores the intersection of pop culture, streaming entertainment, digital trends, and contemporary lifestyle. Her weekly commentary reaches thousands of culture enthusiasts.
