Is Trazodone Addictive? Medical Facts, Dependency Risks, and Side Effects
 By Alexander Ross
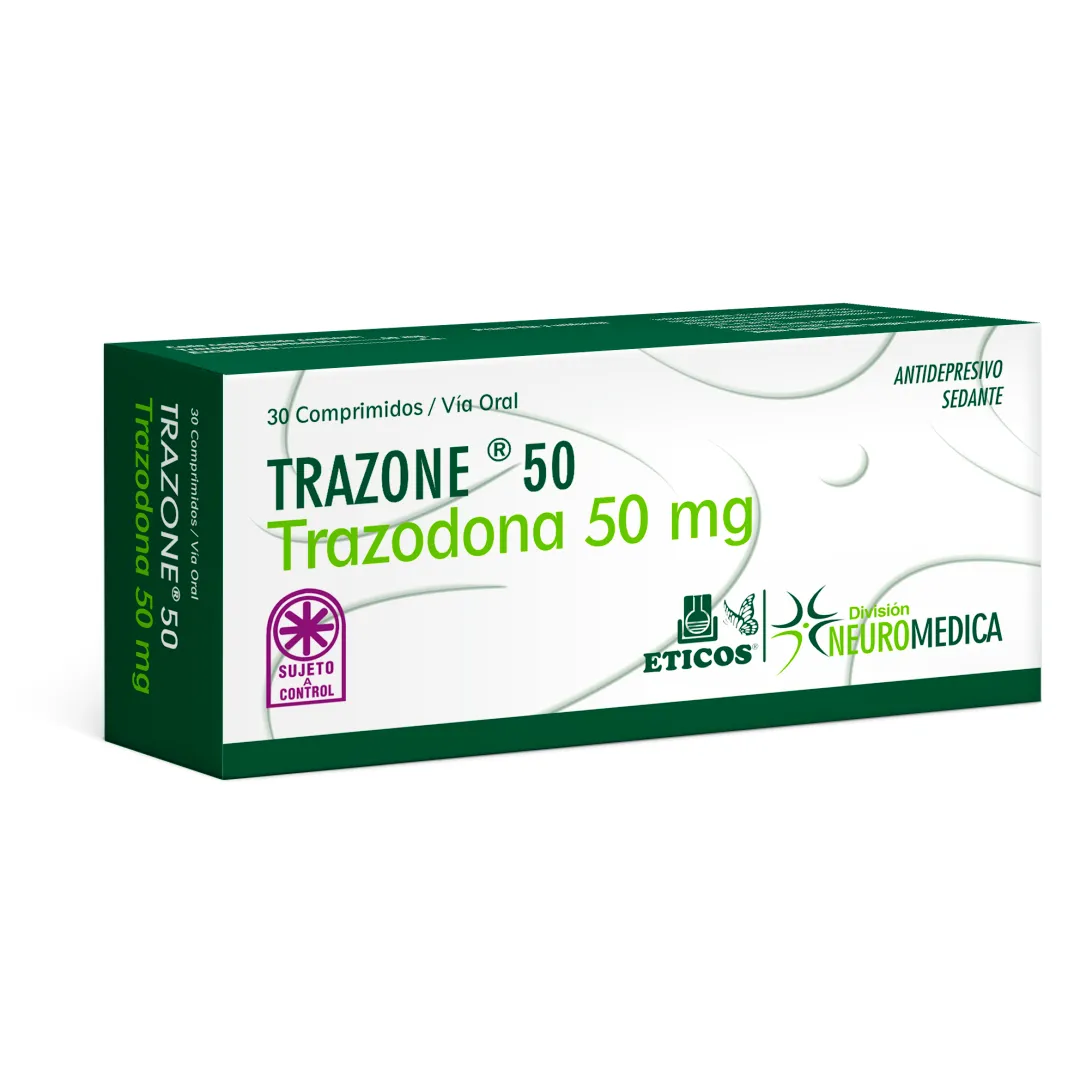
Italian researchers synthesized trazodone in 1966 under the hypothesis that depression stemmed from psychological pain thresholds rather than simple neurotransmitter deficits. The US Food and Drug Administration approved the compound in 1981 for major depressive disorder. It represented the first member of the serotonin antagonist and reuptake inhibitor (SARI) class, distinguishing itself from tricyclic antidepressants and early monoamine oxidase inhibitors by offering a marginally better cardiac safety profile.
Commercial success as an antidepressant was short-lived. Patients taking the therapeutic 150 mg to 400 mg daily doses required to lift mood reported overwhelming exhaustion. They could barely keep their eyes open at work. When Prozac and subsequent selective serotonin reuptake inhibitors (SSRIs) arrived in the late 1980s, trazodone lost the depression race almost overnight.
Clinicians, however, noticed an unintended asset. Rather than discarding the compound, prescribers inverted its greatest flaw into a feature. At micro-doses ranging from 25 mg to 50 mg, trazodone bypasses strong antidepressant reuptake mechanics while aggressively shutting down 5-HT2A serotonin receptors, alpha-1 adrenergic receptors, and H1 histamine receptors. The result is rapid sedation without the rapid tolerance patterns typical of conventional sleep hypnotics. Today, off-label prescription accounts for roughly 85% of all trazodone dispenses nationwide.
Alexander Ross has covered the video game industry for a decade, writing deep dives on game design, esports tournaments, VR developments, and gaming culture.
