Complete Guide to Rales Breath Sounds: Causes, Symptoms, and Care
 By Elena Rostova
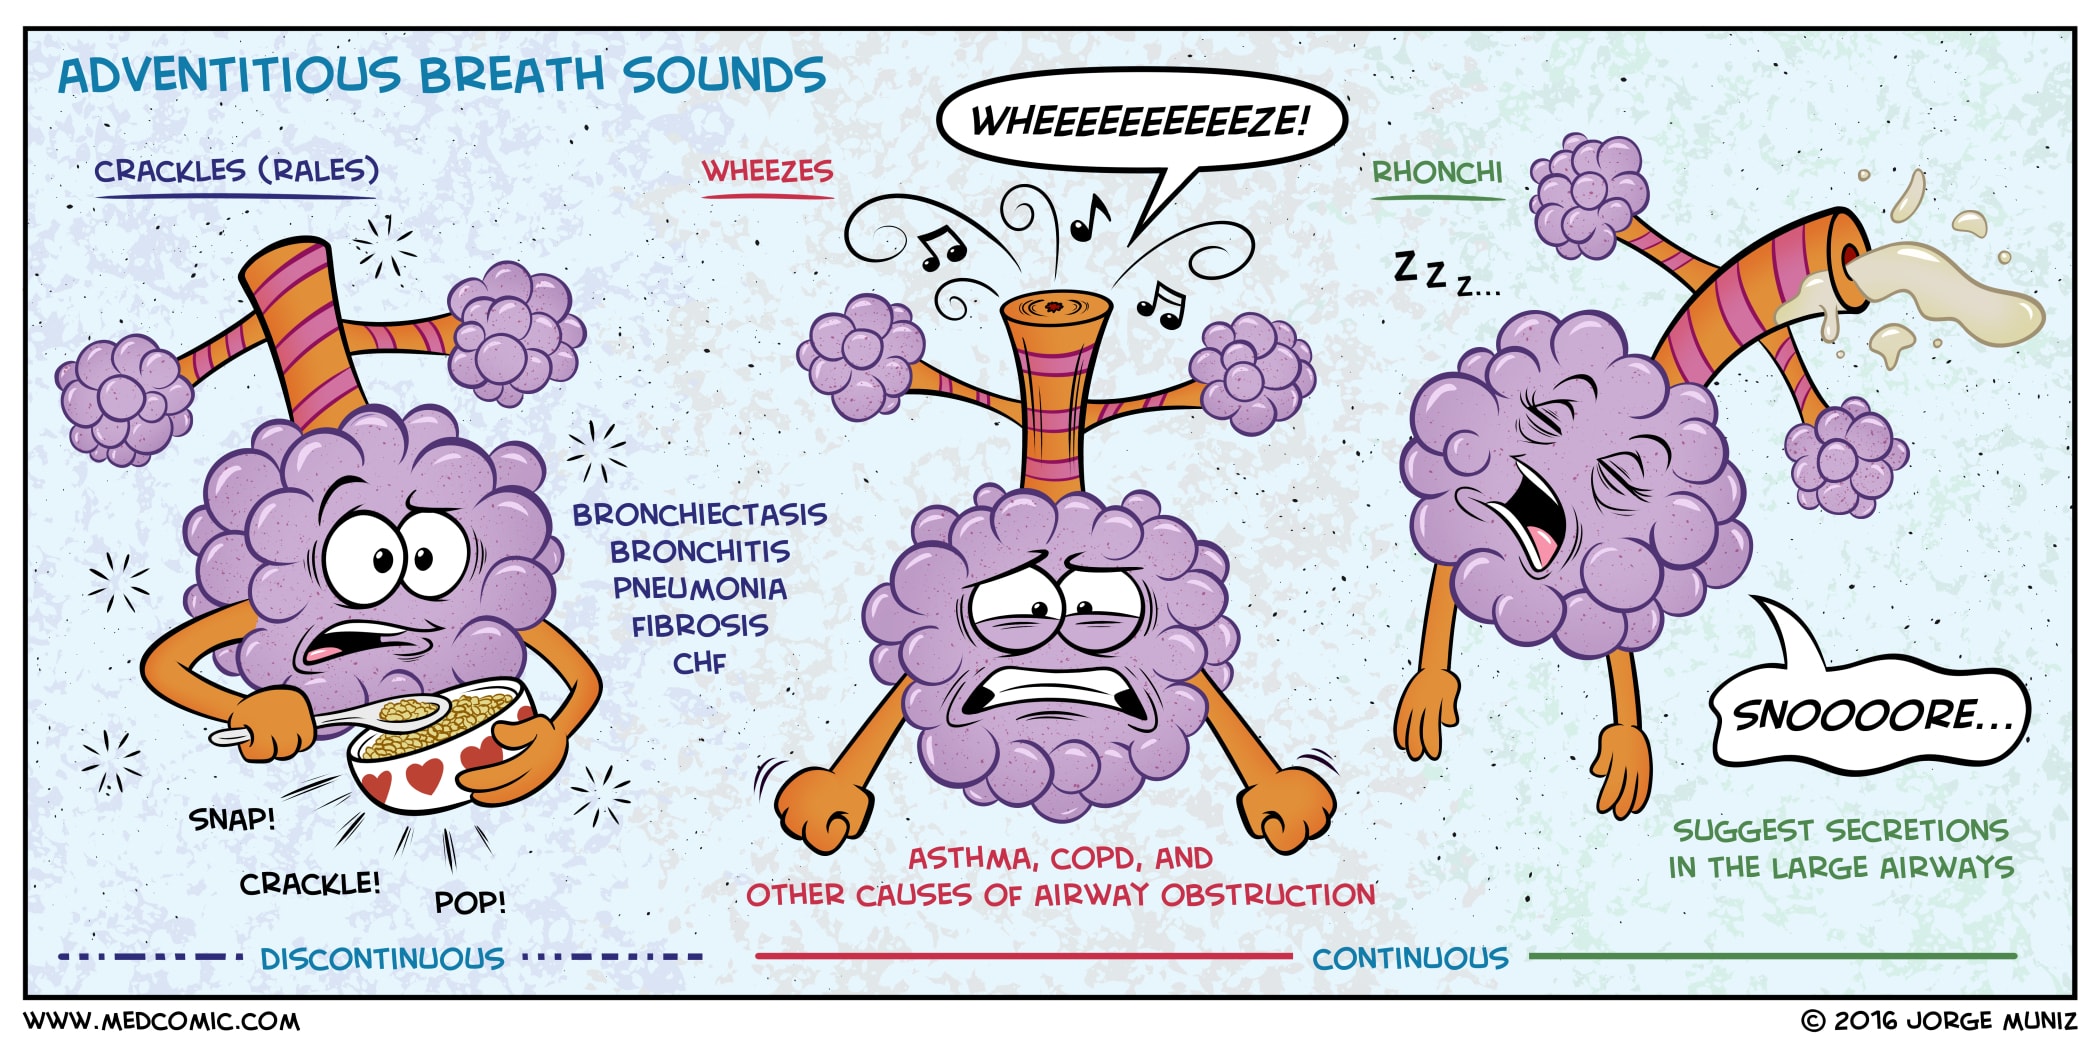
Rales are acoustic warnings, not diagnoses. Treatment must target the underlying driver rather than suppressing the noise itself.
Cardiogenic pulmonary edema demands rapid volume reduction and preload reduction. Intravenous loop diuretics like furosemide drop hydrostatic pressure, while supplementary oxygen or continuous positive airway pressure (CPAP) keeps fluid-laden alveoli recruited. Vasodilators such as nitroglycerin reduce cardiac afterload in hypertensive crises, quickly reducing pulmonary congestion.
Bacterial pneumonia requires targeted antimicrobial therapy based on community-acquired or hospital-acquired risk stratification. Supplemental humidified oxygen helps alleviate hypoxemia, while chest physiotherapy aids in mobilizing thick endobronchial exudates.
For COPD exacerbations featuring rales, therapy shifts to inhaled short-acting beta-2 agonists combined with anticholinergics to open constricted passages, oral or intravenous systemic corticosteroids to reduce mucosal swelling, and controlled supplemental oxygen. Clinicians avoid high-flow unmonitored oxygen to prevent hypercapnic respiratory failure.
When crackles reflect passive atelectasis, pharmacological intervention is unnecessary. Early ambulation, routine deep-breathing exercises, and flutter-valve devices re-expand collapsed lung tissue and eliminate abnormal sounds within hours.
Elena Rostova holds a Master's degree in Public Health Journalism. She covers groundbreaking medical research, holistic wellness trends, mental health awareness, and nutritional science.
