Agap Blood Test Reference Ranges: Normal Chart Values and How to Read Them
 By Sarah Jenkins
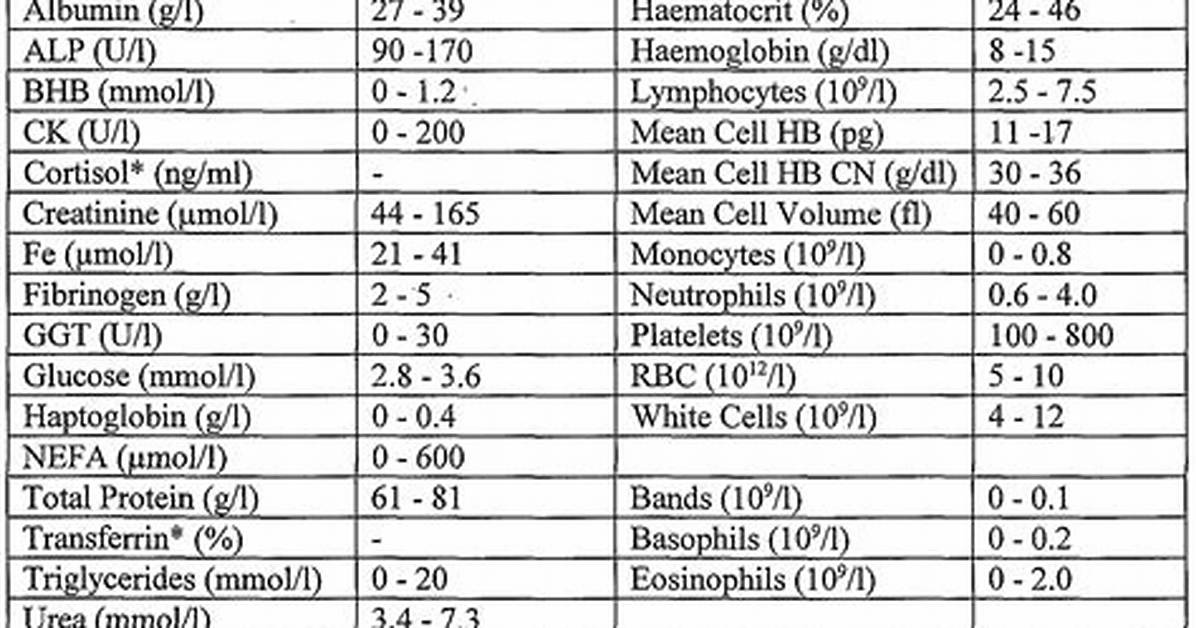
Discovering an unexpected flag on an outpatient chart warrants structured medical evaluation rather than hasty self-diagnosis. A single elevated or depressed number rarely tells an entire story without clinical context.
Physicians first determine whether the patient exhibits acute symptoms: shortness of breath, continuous vomiting, abdominal pain, sudden confusion, or profound lethargy. If acute signs are absent, physicians often order a repeat venipuncture. Lab errors do happen. Delayed transport to the analyzer can permit red blood cells to degrade, altering serum bicarbonate concentrations. Prolonged tourniquet application can also artificially warp localized electrolyte readings.
When repeated testing confirms the imbalance, diagnostic investigations proceed methodically:
- Measuring blood lactate confirms or rules out systemic hypoperfusion.
- Checking capillary blood glucose along with urine or serum ketones evaluates ketoacidosis.
- Assessing glomerular filtration rate and serum creatinine clarifies whether declining kidney filtration plays a role.
- Running blood gas analysis (venous or arterial) measures blood pH directly, confirming whether systemic acidosis is actively underway.
Resolving the underlying disturbance normalizes the calculated gap. Fluid resuscitation clears transient lactic buildups, insulin therapy halts ketoacid production in diabetic crises, and targeted dialysis extracts retained metabolic acids in renal failure.
Sarah Jenkins is a veteran tech journalist with over 12 years of experience covering artificial intelligence, mobile innovations, and digital ethics. Her insights have appeared in leading technology publications worldwide.
