Acne Vs. Perioral Dermatitis: Visual Signs and Symptoms Around Your Mouth
 By Alexander Ross
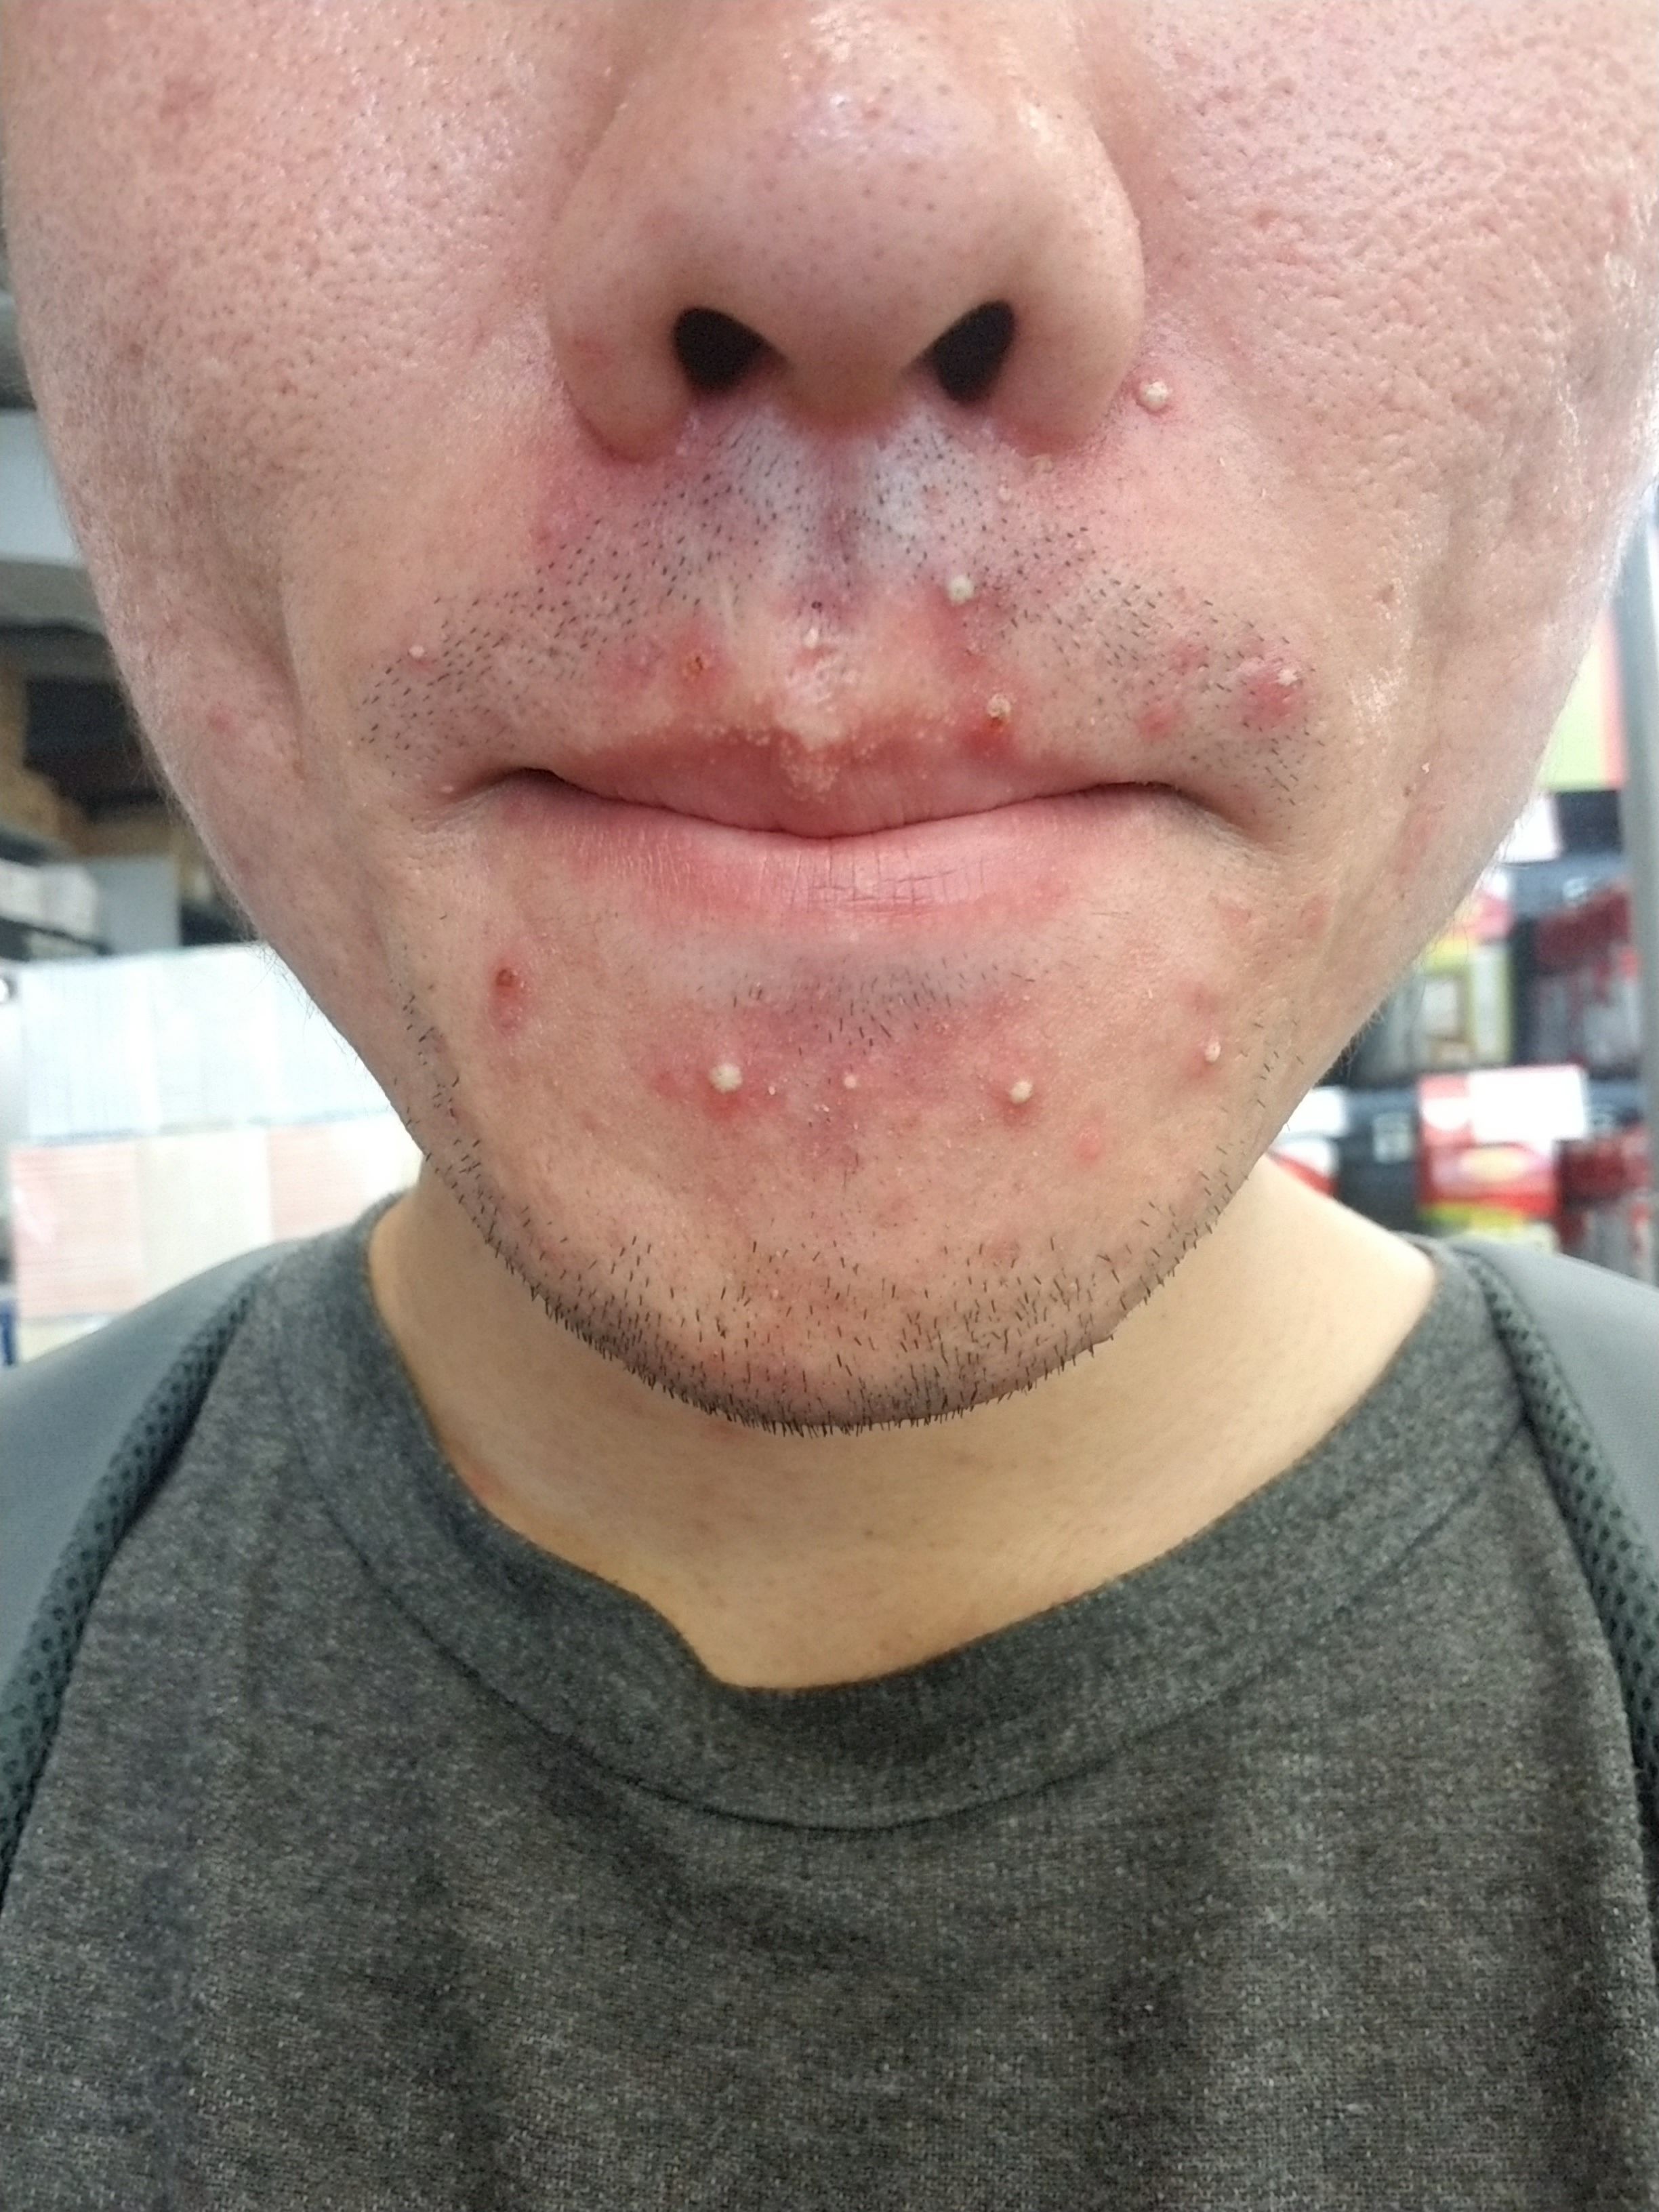
Selecting the correct active ingredient is critical. For genuine acne, proven keratolytic agents clear cellular buildup efficiently. Formulations containing salicylic acid penetrate deep into the lipid-rich pore lining, dissolving accumulated sebum and shedding stuck corneocytes. Pairing a beta-hydroxy acid with a topical retinoid normalizes cellular turnover, gradually eliminating chin and jawline breakouts over an eight-to-twelve-week window.
If the diagnosis is perioral dermatitis, those very same acne treatments create severe flare-ups. Beta-hydroxy acids, benzoyl peroxide, and retinoids inflict devastating mechanical and chemical stress upon the weakened perioral mantle.
The immediate standard of care is "zero therapy", ceasing all active serums, manual exfoliators, fragranced products, and rich facial oils. Patients must switch to lukewarm water and an inert, surfactant-free cleanser.
When topical measures fail to clear the irritation, a formal dermatologist diagnosis becomes indispensable. Board-certified clinicians routinely prescribe anti-inflammatory therapies that quiet follicular reactivity without relying on skin-thinning steroids.
Topical calcineurin inhibitors, such as pimecrolimus or tacrolimus, suppress immune responses without triggering corticosteroid rebounds. Topical metronidazole or azelaic acid at 15% concentration works effectively against both the microbial and inflammatory components of the condition. For severe, persistent cases, a six-to-eight-week course of low-dose oral tetracyclines (such as doxycycline) provides systemic anti-inflammatory benefits, clearing the eruption from within.
Alexander Ross has covered the video game industry for a decade, writing deep dives on game design, esports tournaments, VR developments, and gaming culture.
